
Chapter 5: Prenatal Development and Birth
Newborn Assessment and Risk
Newborn Assessment and Risk
Assessing the Newborn
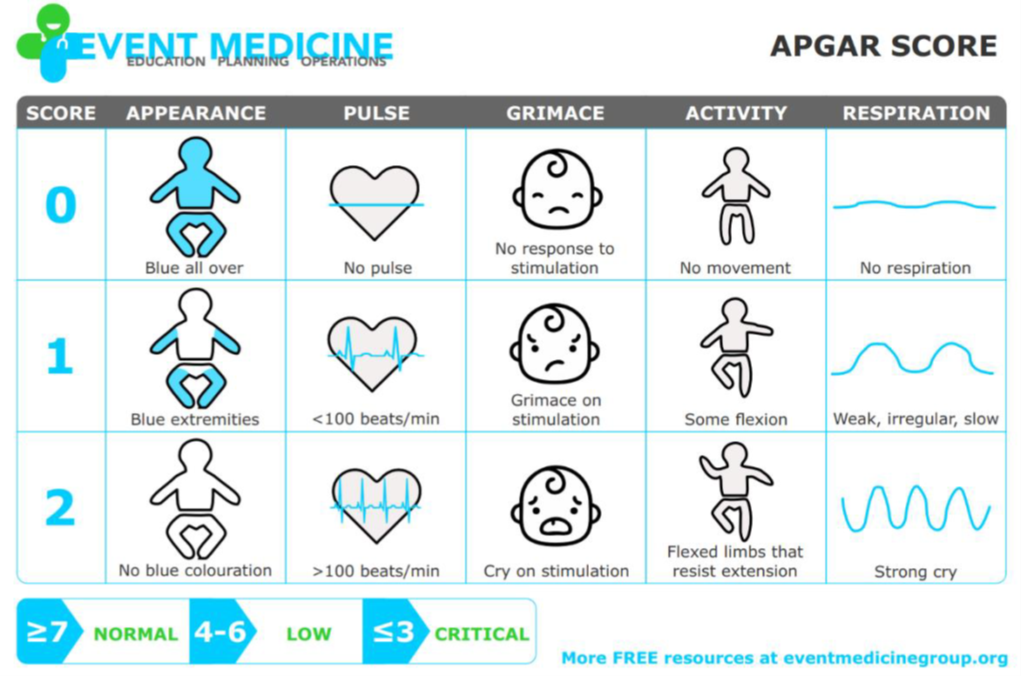
In the minutes following birth, a newborn must undergo dramatic systemic changes to be able to survive outside the womb. An obstetrician, midwife, or nurse can estimate how well a newborn is doing by obtaining an APGAR score. The Apgar score was introduced in 1952 by anesthesiologist Dr. Virginia Apgar as a method to assess the effects on the newborn of anesthesia given to the laboring mother. Healthcare providers now use it to assess the general wellbeing of the newborn, whether or not analgesics or anesthetics were used.
Five criteria are assessed:
- Skin color
- Heart rate
- Reflex,
- Muscle tone
- Respiration
Each criterion is assigned a score of 0, 1, or 2. Scores are taken at 1 minute after birth and again at 5 minutes after birth. Each time that scores are taken, the five scores are added together. High scores (out of a possible 10) indicate the baby has made the transition from the womb well, whereas lower scores indicate that the baby may be in distress. The technique for determining an APGAR score is quick and easy, painless for the newborn, and does not require any instruments except for a stethoscope.
Of the five APGAR criteria, heart rate and respiration are the most critical. Poor scores for either of these measurements may indicate the need for immediate medical attention to resuscitate or stabilize the newborn. In general, any score lower than 7 at the 5-minute mark indicates that medical assistance may be needed. A total score below 5 indicates an emergency situation. Normally, a newborn will get an intermediate score of 1 for some of the APGAR criteria and will progress to a 2 by the 5-minute assessment. Scores of 8 or above are normal.
Video 5.7 APGAR Score explains how to calculate the APGAR score for a newborn.
Recently, discourse surrounding the inaccurate use of the APGAR scale with children of color has gained momentum. Numerous studies have pointed to disparities in the scores assigned to infants with darker skin tones (e.g., Grünebaum et al., 2023; Fair et al., 2025; Jackson, 2025). One of the most obvious issues is with the APGAR scale’s use of “pink appearance” as the criterion for healthy appearance. Some training and education programs have begun incorporating a wider range of healthy outcomes to better capture the well-being of infants from different racial or ethnic backgrounds, but this is not yet widespread, leading to groups like the NAACP calling for all healthcare institutions and entities to enhance their training programs (NAACP, 2025).
Another way to assess the condition of the newborn is by administering the Neonatal Behavioral Assessment Scale (NBAS) developed by Brazelton in the 70’s. This scale contains 28 behavioral and 18 reflex items that assess the baby’s capabilities across different developmental areas (autonomic, motor, state, and social-interactive systems) and describes how infants integrate these areas as they adapt to their new environment. At the time it was developed in the 70’s, the approach was considered innovative for recognizing that a baby is a highly developed organism, even when just newly born. Today, this tool has been used around the world to further assess the newborn, especially those with low Apgar scores, and to make comparisons of infants in different cultures (Brazelton & Nugent, 1995).
In addition to the Apgar and the Neonatal Behavioral Assessment, newborns are also routinely screened for different conditions. Within the first 24 to 48 hours after birth, babies born in hospitals undergo a simple heel stick test, where a few drops of blood are collected on a special paper card. Providers test those dried blood spots for a variety of different congenital disorders, or conditions that are present when the baby is born. In California, newborns are now screened for 80 different genetic and congenital disorders. Newborns are also screened for hearing disorders and certain serious heart problems.
Complications of the Newborn
Low Birth Weight
We have been discussing a number of teratogens associated with a low birth weight such as cocaine, tobacco, etc. A child is considered to have a low birth weight if they weigh less than 5.8 pounds (2500 grams). About 8.52 percent of babies born in the United States are of low birth weight and 1.4 percent are born very low birth weight. A low birth weight baby has difficulty maintaining adequate body temperature because it lacks the fat that would otherwise provide insulation. Such a baby is also at more risk of infection. And 67 percent of these babies are also preterm which can make them more at risk for a respiratory infection. Very low birth weight babies (2 pounds or less) have an increased risk of developing cerebral palsy. Many causes of low birth weight are preventable with proper prenatal care.
Premature Birth

A child might also have a low birth weight if they are born prematurely. A preterm infant (premature or preemie) is any newborn born before 37 weeks’ gestation and weighing less than 5.5 lb. There are many risk factors associated with a premature birth, including the following maternal characteristics (CDC, 2024a):
- having already had a preterm child
- getting pregnant quickly after a previous birth (typically within a year)
- having health issues such as diabetes or high blood pressure
- using drugs or being a regular smoker
- being pregnant with multiples (i.e., twins, triplets, etc.)
- being younger than eighteen years or older than thirty-five years
- having issues with the placenta, such as placenta previa, placental abruption, or bleeding
- having low socioeconomic status and/or food insecurity (lacking access to food of sufficient quantity or quality)
Infants born before 28 weeks are at the greatest risk and require substantial medical care, usually from medical specialists called neonatologists, to have a chance of survival. Their lungs are not yet fully developed, and they did not have the time to develop the normal layer of body fat, so they may require help, such as the use of a ventilator, oxygen hood, or CPAP machine to assist in breathing, a feeding tube, and a special incubator for warmth (Figure 5.11). They must also be monitored to ensure they have enough oxygen in their blood. These infants are at higher risk of having health problems that last a lifetime. Issues associated with being born prematurely and underweight are some of the leading causes of infant death.
Anoxia and Hypoxia
One of the leading causes of infant brain damage is lack of oxygen shortly after birth. Hypoxia occurs when the infant is deprived of an adequate amount of oxygen, leading to mild to moderate brain damage. Anoxia occurs when the infant undergoes a total lack of oxygen, which can lead to severe brain damage. This lack of oxygen is typically caused by umbilical cord problems, birth canal problems, blocked airways, and placenta abruption. Both hypoxia and anoxia can lead to cerebral palsy and a host of other medical disorders.
Check Your Understanding
A measure to determine how well a newborn is doing after birth
28 behavioral and 18 reflex items, that assess the baby’s capabilities across different developmental areas (autonomic, motor, state, and social-interactive systems) and describes how infants integrate these areas as they adapt to their new environment
a state of underdevelopment, particularly in an infant born before it has completed the full gestational period of a normal pregnancy. Premature (preterm) infants have low birth weight and are at risk for such complications as respiratory distress syndrome and jaundice. (https://dictionary.apa.org/prematurity)
